Does Enclomiphene Affect Fertility?
Enclomiphene raises endogenous testosterone by acting on the hypothalamic-pituitary axis rather than replacing hormone from outside the body. This is what the published literature says about its effect on sperm production.
Part of the Enclomiphene Treatment Guide- Medically reviewed by
- Dr. Adrian Vaux, MD
- Updated
- 4 August 2026
- Reading time
- 9 min read
- Written by
- Marcus Hale
- Published
- 12 June 2026
- Reviewed
- 1 August 2026

Fertility questions are among the most common reasons men hesitate before starting hormonal therapy.
Key Takeaways
- 01
Enclomiphene works upstream of the testes, so it raises testosterone without the gonadotropin suppression that characterises exogenous testosterone.
- 02
In published trials, sperm concentration was broadly maintained on enclomiphene, while testosterone gel arms showed reductions.
- 03
Exogenous testosterone suppresses LH and FSH and can reduce sperm production, sometimes markedly.
- 04
Fertility intent should be stated before any therapy begins; a baseline semen analysis is ordinarily part of the workup.
Fertility and testosterone
Male fertility depends on a signalling loop rather than a single hormone. The hypothalamus releases GnRH, the pituitary responds with luteinising hormone (LH) and follicle-stimulating hormone (FSH), and those two gonadotropins instruct the testes to produce testosterone and to support spermatogenesis. Anything that quiets that signal tends to quiet sperm production with it.
This is the reason the fertility question comes up so often. Men are frequently told that raising testosterone is straightforward, and in one narrow sense it is — but how testosterone is raised determines what happens to the rest of the axis. Two therapies can move the same number on a lab report and have opposite effects on the testes.
Why exogenous testosterone suppresses the axis
When testosterone is introduced from outside the body, the hypothalamus and pituitary read the circulating level as sufficient and reduce their own output. LH and FSH fall. Intratesticular testosterone — the concentration that actually matters for spermatogenesis — falls with them, even while serum testosterone looks healthy.[4]
How enclomiphene works
Enclomiphene citrate is the trans-isomer of clomiphene, a selective estrogen receptor modulator. It occupies estrogen receptors in the hypothalamus, blunting the negative feedback that oestradiol normally exerts there. The hypothalamus reads less oestrogenic signal, GnRH output rises, and the pituitary follows with more LH and FSH.[2]
- 01Estrogen receptors in the hypothalamus are blocked, reducing negative feedback.
- 02GnRH pulse frequency and amplitude increase.
- 03The pituitary releases more LH and FSH into circulation.
- 04Leydig cells respond with increased endogenous testosterone; Sertoli cell support for spermatogenesis is maintained.
The practical consequence is that the testes remain part of the process. Testosterone production is stimulated rather than substituted, which is why the drug is discussed at all in a fertility context.
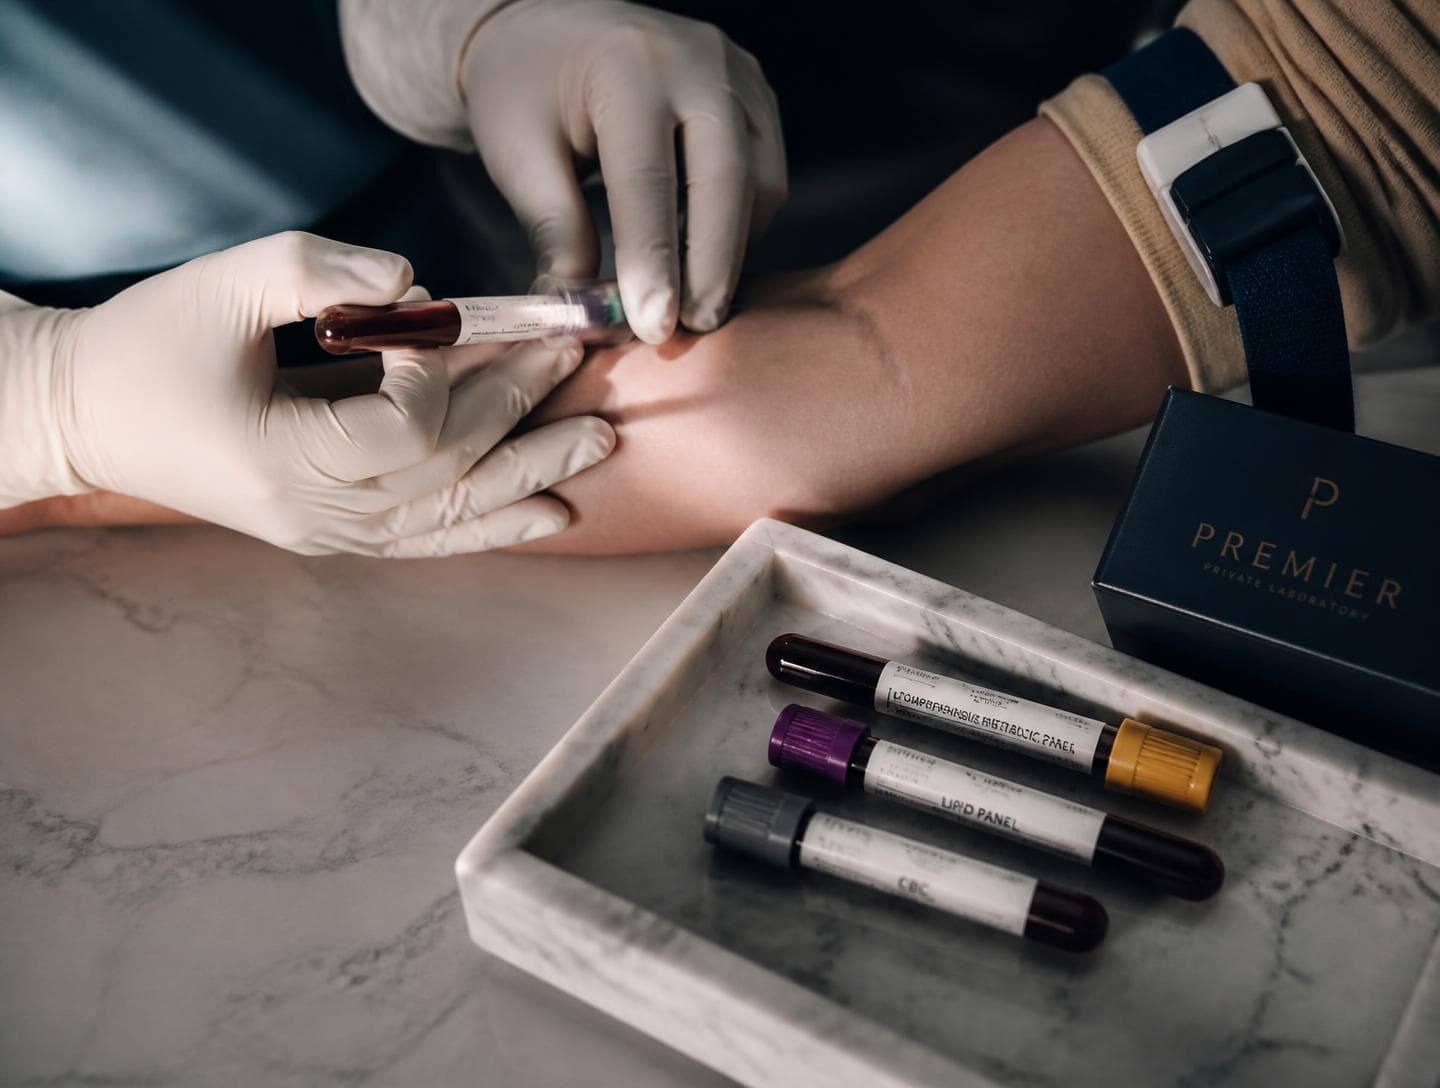
Semen analysis and a baseline hormone panel are ordinarily drawn before any therapy begins.
A note on terminology
Clomiphene citrate is a mixture of two isomers: enclomiphene and zuclomiphene. Zuclomiphene has a longer half-life and more oestrogenic activity. Enclomiphene is the isolated anti-oestrogenic isomer, which is why the two are not interchangeable in the literature. See the enclomiphene treatment profile for the full pharmacology.
Sperm production
Spermatogenesis is slow. A full cycle takes approximately 64 to 72 days, with further time for epididymal transit, which is why semen parameters are conventionally reassessed on roughly a three-month interval rather than weekly.[4] Hormone levels can change within days; semen analysis cannot.
- Concentration — sperm per millilitre of ejaculate, the parameter most often reported in the enclomiphene literature.
- Motility — the proportion moving progressively.
- Morphology — the proportion with normal form.
- Volume — total ejaculate, which varies substantially between samples from the same man.
What the research shows
The most frequently cited comparison is a randomised study of obese men with secondary hypogonadism, in which enclomiphene was measured against topical testosterone. Both arms raised serum testosterone. Only the enclomiphene arm raised LH and FSH, and sperm concentration behaved differently between the two.[1]
Evidence Summary
Gonadotropin response
Kim et al. · BJU International · 2016Enclomiphene citrate raised total testosterone while increasing LH and FSH, in contrast to topical testosterone, which raised testosterone but suppressed both gonadotropins.
Sperm concentration
Kim et al. · BJU International · 2016Across the reported treatment period, sperm concentration was broadly preserved in the enclomiphene arm, whereas the topical testosterone arm showed reductions from baseline.
Secondary hypogonadism
Wiehle et al. · Journal of Sexual Medicine · 2015In men with secondary hypogonadism, enclomiphene normalised morning testosterone in the majority of participants while maintaining testicular function markers.
Reported effects on hormonal and semen parameters
| Parameter | Enclomiphene | Testosterone gel | Untreated baseline |
|---|---|---|---|
| Total testosterone | Increased | Increased | Reference |
| Luteinising hormone (LH) | Increased | Suppressed | Reference |
| Follicle-stimulating hormone (FSH) | Increased | Suppressed | Reference |
| Sperm concentration | Broadly maintained | Reduced | Reference |
| Oestradiol | Modest increase | Variable | Reference |
Directional summary of findings reported in the cited trials. Individual results vary. [NEEDS CITATION for pooled magnitudes]
Preserving gonadotropin signalling is the entire point. If a man tells me he may want children, that changes the treatment conversation before we discuss any number on his panel.

Enclomiphene vs TRT
Both approaches address low testosterone; they are not substitutes for one another. Testosterone replacement is well established, tightly titratable, and appropriate for many men — including men with primary testicular failure, where stimulating the pituitary would achieve nothing. Enclomiphene depends on a testis that can still respond.
Clinicians should discuss the potential effect of testosterone therapy on spermatogenesis with men who are considering fertility.
Endocrine Society, clinical practice guideline
The choice is therefore diagnostic rather than preferential. It depends on where the deficiency originates, what the gonadotropins are doing at baseline, and whether fertility is a stated priority.[5]

Follow-up intervals are set by the prescribing physician.
Clinical considerations
Enclomiphene is not FDA-approved for male hypogonadism or for infertility. Prescribing it for either is an off-label clinical judgement, made with a specific patient in front of the clinician.
- Fertility intent should be raised at the first consultation, not after therapy begins.
- Oestradiol rises on SERM therapy in some men and is monitored rather than assumed benign.
- Visual disturbance is a recognised class effect of SERMs and warrants prompt review.
- Therapy is reassessed on a defined interval; continuation is not automatic.
Sources & References
Every figure and claim in this article traces to one of the references below.
- 1.
Kim ED, McCullough A, Kaminetsky J. Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone.
BJU International2016Peer-revieweddoi:10.1111/bju.13337 - 2.
Wiehle RD, Fontenot GK, Wike J, et al. Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial.
Journal of Sexual Medicine / Fertility & Sterility2014–2015Clinical trialdoi:10.1016/j.fertnstert.2014.04.021 - 3.
U.S. Food & Drug Administration. Clomiphene citrate prescribing information and class labelling for selective estrogen receptor modulators.
FDA2024Regulatoryaccessdata.fda.gov - 4.
Mulhall JP, Trost LW, Brannigan RE, et al. Evaluation and management of testosterone deficiency: AUA guideline.
American Urological Association2018 (amended 2024)Clinical guidelineauanet.org - 5.
Endocrine Society. Testosterone therapy in men with hypogonadism: clinical practice guideline.
The Endocrine Society2018Institutionalacademic.oup.com

Marcus Hale
Senior Clinical Editor, Caesar
Marcus writes Caesar's endocrinology and men's health reference material. He has covered clinical research for over a decade and works directly with the review panel on every hormonal therapy explainer.

Dr. Adrian Vaux, MD
Board-certified Urologist · Male Reproductive Endocrinology · Andrology & Fertility
Dr. Vaux reviews Caesar's fertility and hormonal therapy material for clinical accuracy. He practises male reproductive medicine and has published on gonadotropin response to SERM therapy.
Medically reviewed 1 August 2026

Reading informs. Data decides.
A 40+ marker panel and a licensed physician reading it decide whether treatment is indicated — an article can't.
Not live in preview
Frequently Asked
Short answers to the questions readers send about enclomiphene and fertility. Each one is hedged the same way the article is.
Fertility and hormone questions are personal. A physician can review your labs and discuss whether enclomiphene fits your situation.
Not live in preview
Where To Go Next
Does Enclomiphene Affect Sperm Count?Preview content · not yet available

How LH and FSH Affect Male FertilityPreview content · not yet available

Enclomiphene Side Effects, In Reported FrequencyPreview content · not yet available

How Long Does Enclomiphene Take To Work?Preview content · not yet available

Enclomiphene vs TRT: What The Data SeparatesPreview content · not yet available

Why Testosterone And Metabolic Markers Move TogetherPreview content · not yet available
Editorial & Medical Notice
Caesar publishes educational reference material. It is not a diagnosis, a prescription, or a promise of an individual result. Treatment decisions belong to you and a licensed physician who has reviewed your history and laboratory work. Our content is written by our editorial team, cited to primary literature, reviewed by a licensed clinician, and re-reviewed on a fixed schedule.